

If you are building or scaling a digital health product, this core tension is already familiar: the demand for mental health support continues to grow, but qualified clinicians, budget, and infrastructure cannot keep up. When we talk about AI in mental health, it is no longer an imaginary future — rather, it is the infrastructure layer that progressive health organizations are investing in now.
The world is experiencing the growing burden on mental health systems, and 85% of the people with mental health conditions go untreated globally — held back by financial barriers, a shortage of providers, geographic gaps, and the persistent stigma around seeking help. There’s a growing rate of anxiety, depression, and stress-related disorders. WHO data show that they have increased significantly during and after the pandemic by around 25-27%.
In this article, you’ll learn:
- Where AI creates the most measurable clinical and operational value
- Which use cases are production-ready versus still experimental
- What a compliant, secure AI mental health architecture looks like
- How Geniusee has already built and deployed AI-powered wellbeing tools in practice
If you’re evaluating AI readiness before committing to a build, our AI consulting team can help you scope a responsible path forward.
Key takeaways
- Gaps in access to care are expanding as demand continues to outpace the supply of professionals, affecting treatment rates worldwide.
- Approximately 65% of clinics have implemented AI-based risk stratification models to identify patients at elevated risk of self-harm and enable earlier intervention.
- The progress in ML and NLP enables more sophisticated screening and monitoring than rule-based digital tools could ever provide.
- Automation of routine procedures, earlier identification of risk indicators, and continuous follow-up between visits will improve care delivery.
Why mental health systems require AI today
Market and systemic pressure
The mental health labor force is overburdened in most nations. Millions of people in the U.S. reside in areas where there are not enough mental health professionals, and numerous psychologists cannot take new clients, which causes them to have a long wait list. Untreated mental health challenges cut across the world, and the impediments, such as cost, shortage of providers, and stigma, don’t allow many people to seek help, as most people with symptoms have not received care.
Systemic bottlenecks are caused by these pressures:
- Clinician shortages mean that regular appointments are increasingly rare, and crisis intervention becomes a distant reality.
- The post-pandemic surge in anxiety and depression has intensified the need for faster assessment and care, prompting the adoption of AI tools. They are already used by 44% of psychologists for clinical documentation and administrative tasks, freeing up time for patients.
- Digital therapy programs are useful, but many continue to have high dropout rates without a continuous engagement strategy.
- Administrative burden consumes clinician time that would otherwise be used for direct care.
- The manual triage and documentation process slows response time and increases the wait time for high-risk patients.
- Fragmented data across electronic health records (EHRs), telehealth platforms, and wearables makes early detection nearly impossible without automated integration.
Gaps in operations that AI can help solve
Healthcare systems require instruments that ensure capacity expansion without compromising safety and quality. The tangible enhancements of AI include:
Early detection and screening
Predictive analytics and advanced NLP interfaces can read patient text messages or dialogue indicators of distress, risk, or worsening mental health and assist clinicians in prioritizing outreach before symptoms get out of control.
Risk prediction and suicide prevention
Certain AI algorithms can identify behavioral patterns associated with suicidal ideation and increased risk, allowing the triage systems to prioritize urgent cases and consider them more quickly.
Individualized matching of treatment
By analyzing information from symptom combinations, treatment history, and behavior patterns, AI can assist the clinician in adjusting the therapy plan rather than using a one-size-fits-all approach.
Ongoing individual inter-session monitoring
Wearables, digital phenotyping, and periodic measurements can be incorporated into AI systems that track mood, sleep, and activity patterns and signal care teams when trends indicate increased risk or disengagement.
What are AI use cases in mental health?
AI-based screening and early diagnosis
One of the greatest bottlenecks in mental health is screening. The intake assessments are usually manual, imprecise, and sluggish. AI systems enhance this step by evaluating unstructured patient inputs in real time.
Current production-ready screening capabilities include:
- Natural language processing (NLP) systems that evaluate free-text intake responses and identify linguistic markers associated with depression, anxiety, and suicidal ideation
- Voice analysis tools that assess tone, speech pace, and stress signals during telehealth visits
- Behavioral signal analysis that measures response latency, engagement patterns, and changes in digital interaction frequency
- Risk scoring models that aggregate these inputs into probability scores, helping clinicians triage high-risk cases more quickly
The effect on the business is quantifiable. AI-powered intake automation reduces assessment time and enhances triage efficiency. The risk of escalation and the likelihood of hospitalization are reduced with earlier intervention. Most of all, a final diagnostic decision is left in the hands of clinicians.
Clinical Decision Support Systems (CDSS)
Psychiatric therapy usually incorporates repetitive drug dosages. This variability in response complicates standardized pathways. Clinical decision support systems reduce uncertainty by synthesizing past and current data.
What CDSS tools do in mental health:
- Treatment recommendation models examine prior outcomes and symptom clusters to suggest evidence-aligned therapy pathways
- Outcome prediction algorithms estimate the probability of response to different treatment approaches
- Medication risk models flag likely side effects based on individual patient characteristics
- Polypharmacy interaction checkers — particularly valuable for patients managing comorbid physical and mental health conditions
CDSS tools remain advisory. Licensed professionals are always the ones to make the final decisions.
Conversational AI and digital therapeutics
Conversational AI in mental health has moved well beyond appointment scheduling. Large language model (LLM)-driven therapy assistants now operate within structured therapeutic frameworks — most commonly cognitive behavioral therapy (CBT) — in regulated settings.
Validated use cases for conversational AI in mental health:
- Guided CBT programs that walk patients through exercises and reflective prompts
- Between-session check-ins that track mood changes and flag deterioration
- Structured psychoeducation modules covering coping strategies, medication awareness, and self-management
- 24/7 crisis triage systems that detect distress signals in user inputs and route them to human responders
Important limitations apply. Conversational AI cannot substitute for a licensed therapist. In many jurisdictions, advanced systems are regulated as medical devices. Any deployment must include clear escalation pathways and human oversight for high-risk situations.
Predictive risk modeling
Risk prediction is one of psychiatry’s hardest problems — and one where AI is showing real clinical value. According to recent studies, approximately 65% of health systems implementing AI risk stratification report improved early identification of patients at elevated risk of self-harm.
How predictive models work in mental health:
- Machine learning models assign risk levels based on historical clinical patterns
- Time-series modeling tracks symptom trajectories over weeks and months
- Multimodal systems combine EHR records, behavioral data from wearables, and communication patterns
- Reinforcement learning approaches that adapt risk thresholds based on individual patient response histories
Applications include suicide risk prediction, relapse prediction, and hospital readmission forecasting. Early warning systems allow care teams to intervene before crisis thresholds are breached — reducing emergency department load significantly.
Prediction models require continuous monitoring for bias and drift. False positives cause unnecessary distress. False negatives can be catastrophic. Both must be tracked systematically.
Behavioral analytics and remote monitoring
Mental health deterioration rarely happens suddenly. It builds gradually across sleep patterns, activity levels, communication frequency, and emotional tone. Remote monitoring tools give care teams continuous visibility into those signals — not just a snapshot at a scheduled appointment.
Data sources that feed behavioral AI monitoring:
- Smartphone usage patterns — changes in communication frequency, app engagement, and movement
- Wearable devices tracking sleep disturbances, heart rate variability, and physiological stress indicators
- Voice biomarkers that detect subtle changes in affect across calls or recorded check-ins
- Passive digital phenotyping that aggregates behavioral signals without requiring active patient input
AI methods, including anomaly detection and behavioral drift analysis, identify gradual symptom increases that patients themselves often don’t report. Clinicians receive structured alerts rather than raw data streams. This shifts care from reactive crisis response toward proactive, preventive management.
AI mental health platforms’ technical architecture
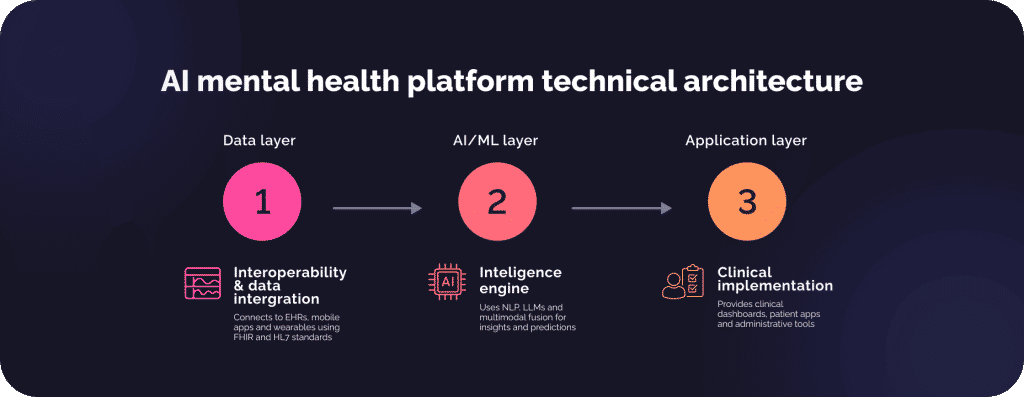
Contemporary mental health AI systems are not just plug-and-play models for applications. They are stacked systems that are created to consume fragmented data, create clinically important insights, and provide them in secure, controlled settings.
Data layer
The basis is interoperability. The AI platforms are connected to electronic health records using FHIR and HL7 standards, allowing access to diagnoses, medications, lab results, and clinical notes in a structured format. It is not possible to integrate AI into the workflow without considering it as a part of care.
In addition to EHRs, there are mobile apps and wearables that provide behavioral and physiological data, such as sleep patterns, activity levels, heart rate variability, and patient-reported mood. These signals are consumed via safe APIs and sent into organized and unstructured data streams.
Since mental health data includes sensitive narrative documentation and even free-text discussions, the platform should accept both structured datasets and unstructured language inputs. All data is usually secured in HIPAA- and GDPR-compliant, encrypted-at-rest and in-transit cloud environments, with limited access controls and an audit trail.
AI/ML Layer
The intelligence engine is above the data layer. NLP pipes can be used to extract meaning out of clinical notes, intake forms, and patient messages. Large language models are fine-tuned on domain-specific psychiatric language rather than using general-purpose outputs.
Advanced systems add:
- Multimodal fusion — combining text, voice, behavioral cues, and biometric signals to improve prediction accuracy
- Explainability (XAI) modules that show clinicians why a risk score was generated and which input signals drove it
- Model monitoring and drift detection systems that continuously review performance so predictions stay valid as patient populations and documentation practices evolve
Application layer
Insights only matter when they reach clinicians and patients in usable form.
- Clinician dashboards display risk stratification, treatment response predictions, and longitudinal symptom trends in a clear, actionable format.
- Patient-facing mobile apps support mood tracking, digital CBT delivery, secure messaging, and passive data collection.
- Administrative automation tools handle documentation, intake processing, and coding support — reducing clinician burnout.
- API integrations connect AI platforms with telehealth systems to ensure continuity between in-person and remote care.
Compliance and regulatory issues
One of the most sensitive regulatory conditions in healthcare is how AI in mental health works.
U.S. landscape
Any system that processes protected health information must meet HIPAA privacy and security requirements. If AI tools make a diagnosis or treatment recommendation, they can be regulated by the FDA based on their risk outputs and the purpose of their use.
There is a growing skepticism about bias monitoring, especially on models deployed in suicide prediction or risk stratification. The developers must demonstrate their verification, performance stability, and protection against discriminatory results.
EU & UK
In GDPR, mental health information is considered to be highly sensitive personal data and needs explicit consent and rigorous processing requirements. The EU AI Act provides a risk-based classification, and most mental health AI systems would be expected to fall into high-risk categories that should be transparent, documented, and monitored post-market.
When an AI system is involved in clinical decision-making, it may need to be certified as a medical device under the MDR framework in Europe or as a UKCA-marked device under the UK framework.
Key compliance risks
Underrepresented groups can be disproportionately affected by algorithmic bias. Information privacy violations carry legal and reputational consequences. The inability to explain negatively affects clinicians’ faith and regulatory acceptance. The unmonitored use of AI results in an over-dependence on AI results is both legally and ethically vulnerable.
The ethical and clinical AI mental health risks
There are unique clinical stakes when it comes to mental health. False positives of suicide prediction can result in unwanted suffering and excessive intervention, whereas false negatives can be disastrous.
Unless very strictly regulated, generative AI systems can hallucinate false information or give incorrect treatment recommendations. Emotional addiction to AI chatbots can be seen as another issue, especially with teenagers or socially isolated people.
The problem of dataset bias is still significant. Most psychiatric data sets do not represent the minorities sufficiently and may distort predictions. Patient autonomy and trust may be challenged by the over-automation of sensitive decisions that have not been reviewed by a human being, such as involuntary risk escalation.
AI mental health ROI measurement
Healthcare executives are putting more conditions on AI deployment.
Clinical metrics
The indicators include shorter time to diagnosis, higher rates of treatment adherence, and lower levels of crisis escalation. Symptom deterioration can be identified earlier, thereby minimizing the need for emergency interventions.
Operational metrics
The processing time can be significantly reduced through AI-based intake automation. Reducing administrative burden enhances clinician productivity and increases the number of appointments without increasing staff.
Financial outcomes
Some of the best ROI cases are usually motivated by lower hospitalization and lower readmission rates. Through scalable digital therapy programs, it can increase service coverage and manage the marginal cost per added patient. Reduction in clinician turnover costs linked to burnout relief from administrative automation.
Healthcare organization implementation roadmap
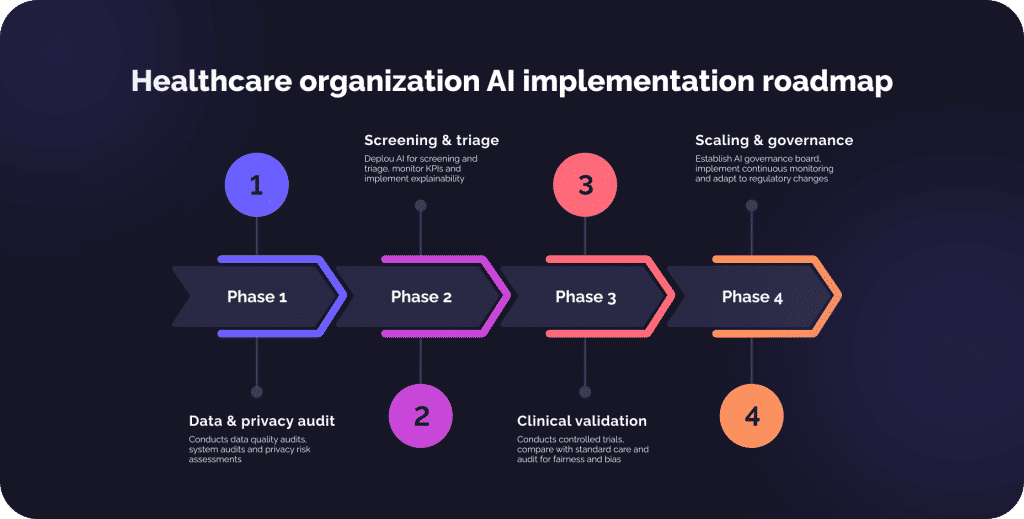
The adoption of AI should be gradual and not an abrupt decision.
- Phase 1:
This starts with data quality audits, integrating system audits, and privacy risk assessment. A lack of a good database compromises predictability.
- Phase 2:
Phase 2 usually begins with screening or triage, during which quantifiable KPIs, such as reductions in response time or improvements in risk detection accuracy, can be identified. Explainability monitoring should be deployed from the very onset.
- Phase 3:
Clinical validation entails controlled trials, comparisons with standard care, and fairness and bias audits across demographic lines.
- Phase 4:
Scaling and governance entail creating an AI governance board, implementing continuous model monitoring, and monitoring changing regulatory requirements.
When AI isn’t the solution in mental health
Acute crisis interventions cannot be handled by AI without immediate human oversight. It must not assign complicated psychiatric diagnoses without clinician validation. The unregulated use of generative AI systems in therapy is an unacceptable risk.
How Geniusee applies AI to mental health and wellbeing use cases
AI-assisted employee well-being check-ins during a crisis
When the full-scale war in Ukraine began in 2022, Geniusee faced a sensitive operational challenge: employees were dispersed across regions and countries, some were relocating, and others were close to active danger zones. The company needed a way to understand team wellbeing without turning support into surveillance.
Geniusee built an internal AI-assisted chatbot for voluntary well-being check-ins. Employees could share short updates about their status and location. The system anonymized and aggregated responses so leadership could see stress patterns and emerging risk areas without exposing individual private details.
Key outcomes:
- Voluntary well-being check-ins for distributed teams
- Aggregated, anonymized welfare trend analysis
- Early visibility into stress signals and operational risk areas
- Human-led follow-up, with AI used only for signal aggregation
- Privacy-aware design for a high-stress crisis environment
This was not a clinical tool and did not diagnose or replace professional support. Its value was in helping human leaders respond faster and more responsibly.
AI mental health literacy trainer
Geniusee also developed the concept of an AI-powered mental health literacy trainer for workplace scenarios. The goal was to help managers and employees respond more safely when colleagues showed signs of distress, anxiety, withdrawal, or trauma-related behavior.
The system allowed users to describe realistic workplace situations and receive structured guidance on how to communicate empathetically, avoid harmful language, maintain boundaries, and know when to escalate to professional help.
A simulation mode lets users rehearse difficult conversations with the AI acting as a colleague in distress. The AI gave feedback on tone, empathy, and boundaries, but it did not diagnose, prescribe, or act as a therapist.
Key outcomes:
- Safe practice environment for difficult wellbeing conversations
- Guidance on language, empathy, escalation, and boundaries
- Scenario analytics showing which mental health challenges appeared most often
- Preventive education for managers and employees
- Strict guardrails against diagnosis or treatment advice
Healthcare document automation: MedTech CRM
For mental health providers, AI value is often operational before it is clinical. Intake forms, billing records, insurance documents, care notes, and reimbursement data create heavy administrative load for already stretched teams.
Geniusee’s MedTech CRM case demonstrates how AI can reduce that burden. The solution uses Document AI and OCR to parse medical bills, insurance documents, and healthcare records, turning unstructured files into structured data for reconciliation, routing, and reporting.
Key outcomes:
– Automated extraction of key healthcare and financial data
– Intelligent document classification and routing
– Reduced manual data entry and processing time
– Real-time reconciliation with banking transactions
– Compliance-ready audit trail and reporting
For mental health organizations, the same architecture can support intake automation, referral processing, claim documentation, and back-office workflows while clinicians remain focused on patient care.
Speech and language analytics capability
Mental health AI often depends on language signals: written intake forms, chat messages, call transcripts, or voice-based check-ins. Geniusee’s speech recognition and analysis work shows relevant capability here, even though it should not be presented as a clinical mental health deployment.
The system captured, transcribed, and analyzed spoken interactions to identify topics, sentiment patterns, and compliance indicators at scale.
Relevant capabilities:
- Speech-to-text transcription
- NLP-based topic and sentiment analysis
- Structured reporting from unstructured audio
- Real-time flagging workflows
- Scalable audio processing pipelines
In a mental health context, this type of capability would require stricter clinical validation, consent, privacy controls, and human oversight before being used for risk detection or care decisions.
Multimodal risk detection architecture
Geniusee’s ShieldViewAI work is not a mental health case, but it demonstrates an architecture relevant to high-risk AI systems: multimodal data processing, risk-level identification, human review, alerts, and searchable evidence.
For mental health platforms, similar architectural patterns can support safer workflows when adapted responsibly: combining structured records, text inputs, voice data, and behavioral signals into clinician-facing alerts rather than autonomous decisions.
Relevant capabilities:
- Multimodal analysis across documents, audio, images, and video
- Risk-level classification and alert generation
- Search across large evidence/data sets
- Human-in-the-loop review workflows
- Secure data processing pipelines
“Building this system taught us that responsible AI in mental health contexts isn’t about replacing human judgment — it’s about giving humans better, faster signal so they can act before problems compound.” — Oles Dobosevych, Head of Data Science/Data Engineering
Conclusion
Mental systems are strained structurally. The level of demand is kept high, clinicians’ abilities remain limited, and disjointed data prevent quicker intervention. AI is not a substitute for therapists or psychiatrists. It’s more of an essential infrastructure layer that enables earlier detection, higher-quality triage, more personalized treatment plans, and more efficient operations.
The beneficiary organizations are not the ones trying out isolated chatbots. They are the ones creating secure, interoperable, explainable AI systems that are directly integrated into clinical processes. When AI is implemented responsibly, with strong governance, shared regulatory oversight, and human control, mental health providers can expand access to care without compromising safety or quality.
By initiating efforts today with a well-defined use case, quantifiable KPIs and systematic validation, healthcare leaders will be in a better position to meet the increasing demand in 2026 and beyond.
If you consider how to design, validate, and implement secure AI solutions for mental health, Сontact us today.
Are medical devices AI mental health software?
It depends on the intended use. If the system makes diagnostic or treatment recommendations, regulators such as the FDA or the EU may classify it as a medical device.
What data do I need to train mental health AI?
They are usually structured clinical records, symptom scales, treatment outcomes, and the high quality of annotated text or speech data. It is essential that there should be diversity in the processes of demographic representation.
What is the way to make AI fair in psychiatry?
In the form of representative training data, subgroup performance assessment, bias audit, and ongoing monitoring after deployment.
How are the AI mental health solutions defined in terms of ROI?
The operational benefits, such as automated documentation, can be observed within a few months, while the clinical and financial ROI from reduced hospitalizations would require long-term outcome monitoring.
Can AI be used for crisis intervention in mental health?
AI can play a supporting role — flagging risk signals, routing high-priority cases to human responders, and maintaining monitoring between appointments. It cannot and should not manage acute crisis intervention without immediate human oversight. Any deployment in high-risk scenarios requires clear escalation protocols and 24/7 human coverage.




















